
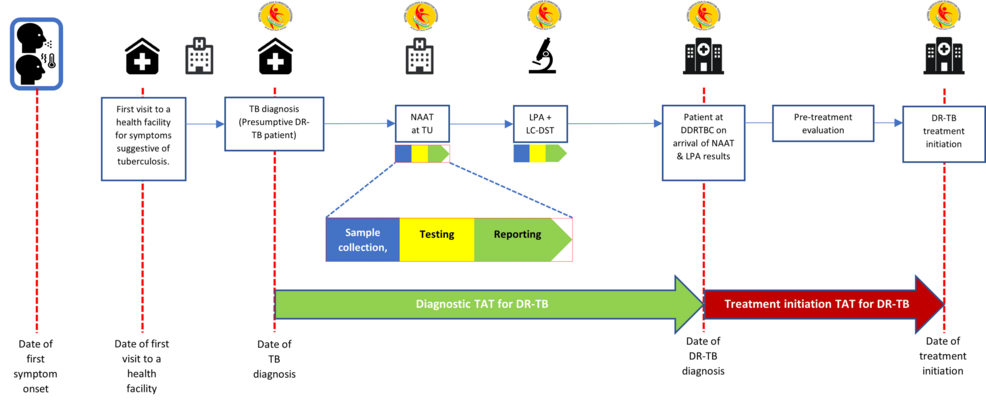
Between October 2021 and June 2022, a mixed-methods study of 158 drug-resistant tuberculosis patients across Delhi and Faridabad districts found that 60.1% experienced diagnostic delays exceeding 15 days, while 33.5% faced treatment initiation delays past seven days.
Understanding the DR-TB Care Pathway
In Plain English: The Clinical Takeaway
- Diagnostic Turnaround Time (D-TAT): Over 60 percent of patients waited longer than 15 days from their initial drug susceptibility testing eligibility to a confirmed diagnosis.
- Treatment Initiation Turnaround Time (TI-TAT): One-third of patients experienced a delay of more than seven days between receiving their diagnosis and actually starting second-line treatment drugs.
- Diagnostic Tool Impact: The use of cartridge-based nucleic acid amplification tests (CBNAAT) was inversely associated with diagnostic delays, whereas reliance on line probe assays (LPA) was associated with longer waiting times.
Diagnostic Delays and Regional Disparities in North India
Drug-resistant tuberculosis continues to represent a severe hurdle for global health elimination frameworks. In 2024, an estimated 390,000 individuals developed multidrug-resistant or rifampicin-resistant tuberculosis (MDR/RR-TB) worldwide, with India bearing 32% of this total disease burden. Under India’s National Tuberculosis Elimination Programme (NTEP), the programme defines diagnostic delay as a turnaround time exceeding 15 days from drug susceptibility testing eligibility to confirmation, and treatment initiation delay as crossing seven days from diagnosis to therapy.
The study conducted at three District Drug-Resistant TB Centres in Delhi and Haryana evaluated 158 newly registered patients. Investigators uncovered a median diagnostic turnaround time of 24 days, with an interquartile range stretching from 7 to 67 days. Meanwhile, the median treatment initiation turnaround time stood at 5 days, ranging from 3 to 11 days. Multivariate logistic regression models demonstrated that diagnostic delay was associated with the use of line probe assays, showing adjusted odds ratios of 6.6. Conversely, the deployment of cartridge-based nucleic acid amplification tests (CBNAAT) was inversely associated with delays, yielding an adjusted odds ratio of 0.2.
Treatment initiation delays showed distinct geographical boundaries. Patients residing in Faridabad faced over three times the odds of delayed treatment start compared to their counterparts in Delhi, registering an adjusted odds ratio of 3.1. Furthermore, younger patients aged 18 years or younger experienced higher odds of treatment initiation delays, with an adjusted odds ratio of 6.4.
| Parameter | Median / Metric | Proportion Affected |
|---|---|---|
| Diagnostic Turnaround Time (D-TAT) | 24 Days (IQR 7-67) | 60.1% experienced delay (>15 days) |
| Treatment Initiation Turnaround Time (TI-TAT) | 5 Days (IQR 3-11) | 33.5% experienced delay (>7 days) |
| Intermediate Diagnostics (LPA Available) | 22.2% of cohort | Associated with aOR 6.6 for diagnostic delay |
| Rapid Testing (CBNAAT Utilisation) | Programmatic integration | Associated with aOR 0.2 (protective against delay) |
Systemic Bottlenecks and Qualitative Barriers
Qualitative findings from in-depth interviews with 16 patients or caregivers alongside 16 programme officials exposed deep-seated operational roadblocks. Participants pointed to insufficient CBNAAT availability, intermediate reference laboratory backlogs, and persistent societal stigma. Additionally, weak private-to-public referral tracking mechanisms frequently trapped patients in prolonged care-seeking loops before reaching designated district centers.
Prolonged intervals before treatment initiation compound clinical risks significantly. Data indicate that delayed therapeutic intervention is associated with more than two-fold higher odds of mortality, while also increasing sputum smear grades and driving secondary resistance to anti-tubercular pharmaceutical compounds. Extending the time to treatment simultaneously prolongs the window of infectivity, fueling ongoing community transmission cycles of drug-resistant strains.
Contraindications & When to Consult a Doctor
Patients undergoing evaluation or treatment for drug-resistant tuberculosis must strictly adhere to prescribed regimens. Self-management, unmonitored treatment interruptions, or the use of unverified alternative therapies are strongly contraindicated due to the high risk of amplifying drug resistance. Individuals experiencing persistent cough, unexplained weight loss, night sweats, or bloody sputum must consult a qualified healthcare provider for rapid molecular diagnostic testing.
Evaluating Public Health Trajectories
Addressing these structural bottlenecks requires expanding decentralized molecular diagnostic infrastructure directly to peripheral levels and strengthening referral mechanisms. These remain vital operational priorities for public health authorities aiming to curb disease transmission and improve treatment success rates across the region.
